
Sudden Vision Loss and EECP: What Does the Evidence Say
Sudden vision loss in one eye is an emergency and must be evaluated immediately. Blockage of the eye's artery is regarded as a type of stroke. EECP has been studied in this condition; however, the evidence is limited and conflicting.
- Non-Surgical
- 35 Sessions
- Painless
Briefly
Supports treatment in patients with sudden vision loss and helps vision to recover.
In sudden vision loss, time is critical. Go to the emergency room or an eye emergency unit without delay.
In a controlled study, EECP did not improve vision in an optic nerve disease causing sudden vision loss.
Evidence is limited and conflicting. EECP does not replace emergency treatment; however, it can be discussed afterward and in selected patients.
What Happens in Sudden Vision Loss?
The eye depends on very fine vessels that nourish the retina. When one of these vessels becomes blocked, or when the blood supply to the optic nerve is impaired, vision can suddenly decrease. The American Heart Association defines blockage of the retinal artery as a type of stroke.
Retina
The retina is the thin layer of the eye that senses light. When it is deprived of blood, its cells can be damaged in a short time.
Optic nerve
The optic nerve carries the image to the brain. Impaired blood supply to it is called ischemic optic neuropathy and usually causes sudden vision loss.
Carotid arteries
Blood to the eye comes from the carotid artery in the neck. Fragments breaking off from plaques here can block an eye vessel.
Hover over or tap the cards: the related area is highlighted in the image.
Heart and rhythm
Clots formed in the heart can also travel to an eye vessel. For this reason, the heart and rhythm are evaluated after sudden vision loss.
Brain
Retinal artery blockage shares the same risk factors as stroke. Afterward, the risk of stroke is also investigated.
Risk factors
Blood pressure, sugar, cholesterol and smoking also affect eye vessels. The guideline recommends rapid screening and treatment of these risks.
Eye Circulation: Before and With EECP
The comparison below simply shows the circulation support targeted with EECP. Its effect in eye disease has not been proven.
Sudden vision loss
- Sudden decrease in vision in one eye
- Lack of blood in the retina or optic nerve
- Heart and vascular risk factors
Circulation support after emergency treatment
- An increase in flow in the head and neck vessels is targeted
- Eye doctor follow-up continues
- Risk factors are treated
This is a schematic illustration. EECP does not replace emergency treatment in sudden vision loss.
How Is EECP Applied?
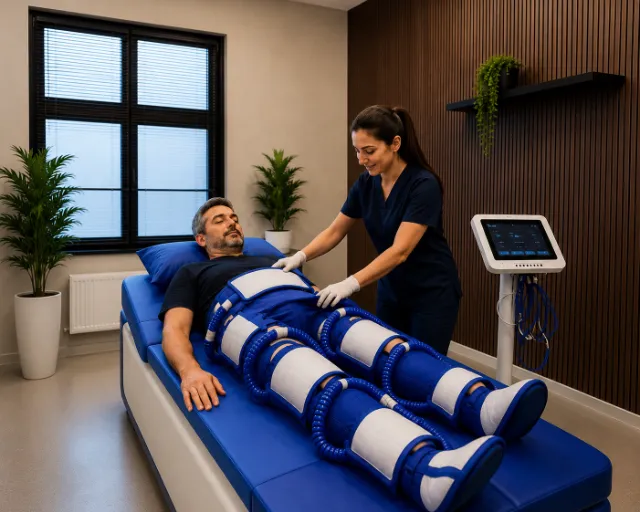
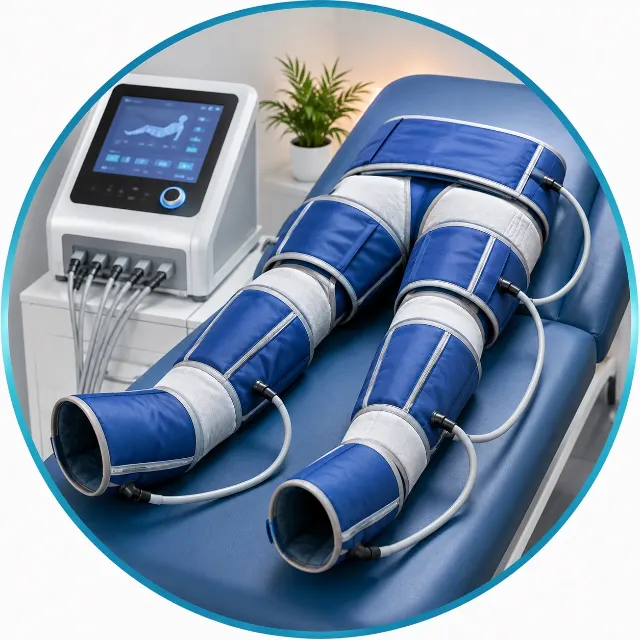
During treatment you lie down and rest. The device monitors your heart rhythm with an ECG and controls the cuffs accordingly.
Cuffs inflate
While the heart relaxes, the cuffs on the calves, thighs and buttocks inflate in sequence: first the calves, then the thighs and buttocks.
Blood heads toward the head
The pressure that rises while the heart relaxes is also reflected in the head and neck vessels. The effect of this on eye circulation varies from person to person.
The heart's workload decreases
The pressure is released just before the heart contracts, so the heart pumps more easily. This cycle repeats with every heartbeat.
Vision is monitored
Before and after the course, visual acuity and visual field are compared by your eye doctor.
What Have the Studies Shown?
Below we summarize the information that stands out in the studies and guidelines. The response varies from person to person.
Emergency
The American Heart Association defines retinal artery blockage as a medical emergency.
Rapid evaluation
The guideline recommends that these patients be evaluated without losing time and directed to treatment.
Non-surgical and painless
It is applied from the outside with cuffs; you lie down and rest throughout the session.
Tolerance
In a study in patients with optic nerve disease, EECP was well tolerated by all patients.
Expert opinion
Experts in China recommend starting EECP as early as possible in retinal artery blockage.
Risk factors
The guideline recommends urgent screening and treatment of vascular risk factors in these patients.
Who Is It Suitable For, and Who Is It Not?
First, an urgent eye and neurology assessment is done; stroke screening and risk factors are addressed. EECP can be discussed only after this stage, together with your eye doctor and our cardiologist.
✓May be suitable for
- Patients with retinal vessel blockage whose emergency assessment and treatment have been completed
- Patients followed by an eye doctor who are suitable from a cardiovascular standpoint
- Patients in whom narrowing of the neck vessels has been found and who want to support vessel health
- Patients who are already suitable for EECP because of heart or vascular disease and who have had an eye vessel problem in the past
✕Not suitable for
- Newly started vision loss: first go to the emergency room immediately
- Severe aortic valve insufficiency
- Aortic aneurysm
- Active deep vein thrombosis or vein inflammation
- Uncontrolled high blood pressure
- severe arrhythmia
- Marked bleeding tendency and pregnancy
How Does the Treatment Process Work?
Blood pressure and pulse are checked before every session. At the end of the course, the results are reviewed with our cardiologist. In eye patients, vision measurements are made on your eye doctor's schedule.
Frequently Asked Questions About Sudden Vision Loss and EECP
What should I do first in sudden vision loss?
Go to the emergency room or an eye emergency unit without delay. The American Heart Association defines this condition as a medical emergency.
Will EECP restore my vision?
We have not read a controlled study showing this. In the controlled study in optic nerve disease, EECP did not improve vision more than the control group.
Why are the heart and brain also examined?
Retinal artery blockage is a type of stroke and shares the same risk factors. For this reason, the heart, rhythm and neck vessels are also evaluated.
When can EECP be considered?
Only after the emergency assessment and treatment are completed, and together with your eye doctor. Because the evidence is limited, expectations are shared openly from the start.
Will I keep taking my medications?
Yes. You need to continue your medications as your cardiologist recommends. The decision to change medication is made only by your doctor.
How many sessions are needed?
The standard course is 35 sessions: 5 days a week, 60 minutes per session. The plan is made in harmony with your eye doctor's follow-up, and vision measurements are repeated regularly.
You May Also Be Interested In




Contact us for a free preliminary assessment
If you are experiencing sudden vision loss, go to the emergency room immediately first. If you are curious about EECP after your treatment, contact us along with your eye and vascular tests; we will discuss expectations openly.
- Non-Surgical
- Painless
- Physician-Supervised
- Nicosia and Morphou